Decades-long ACTIVE study finds brain training lowers dementia risk — speed training with boosters cuts diagnoses by 25%
A 20-year follow-up of the ACTIVE randomized trial finds adaptive speed-of-processing brain training with booster sessions cut dementia diagnoses — including Alzheimer’s — by about 25%, the first long-term trial evidence of such durable protection against cognitive decline.
- Speed training + boosters: Participants receiving adaptive speed-of-processing training with booster sessions showed a ~25% lower incidence of dementia over 20 years.
- Randomized, long-term evidence: ACTIVE is a near-3,000-person randomized trial tracked through medical records and claims, strengthening causal inference.
- Targeted, short intervention: Core protocol: 10 sessions over ~6 weeks with optional boosters (up to 18 sessions over three years); greatest benefit in those completing full booster series.
The study
The trial is the Advanced Cognitive Training for Independent and Vital Elderly (ACTIVE) study, launched in 1998–1999. Key protocol and summaries are available via the ScienceDaily summary and a University of Florida news release.
Participants: About 2,800 adults aged 65–94 at enrollment were randomized to one of three training programs or to a no-training control group.
Interventions: Random assignment to 10 core sessions (60–75 minutes each over ~6 weeks) of either memory, reasoning, or speed of processing training, or to a no-training control. Some participants received booster sessions at 11 and 35 months, for up to 18 sessions over three years.
Main findings
Over a 20-year follow-up, the group that received speed of processing training plus boosters had a statistically significant lower rate of dementia diagnoses compared with controls. The peer-reviewed report appears in Alzheimer’s & Dementia: Translational Research and Clinical Interventions.
Reported outcomes: among people who got speed training + boosters, 40% (105 of 264) developed dementia over 20 years versus 49% (239 of 491) in the control group — a relative reduction of roughly 25%.
What the ACTIVE trial tested
Funded by the National Institutes of Health (NIA/NINR), ACTIVE tested whether brief, structured cognitive training could alter thinking skills and independence in older adults. Nearly 3,000 participants were randomly assigned to:
- Memory strategies: Fixed mnemonic methods for remembering lists and events.
- Reasoning: Problem-solving and pattern recognition exercises.
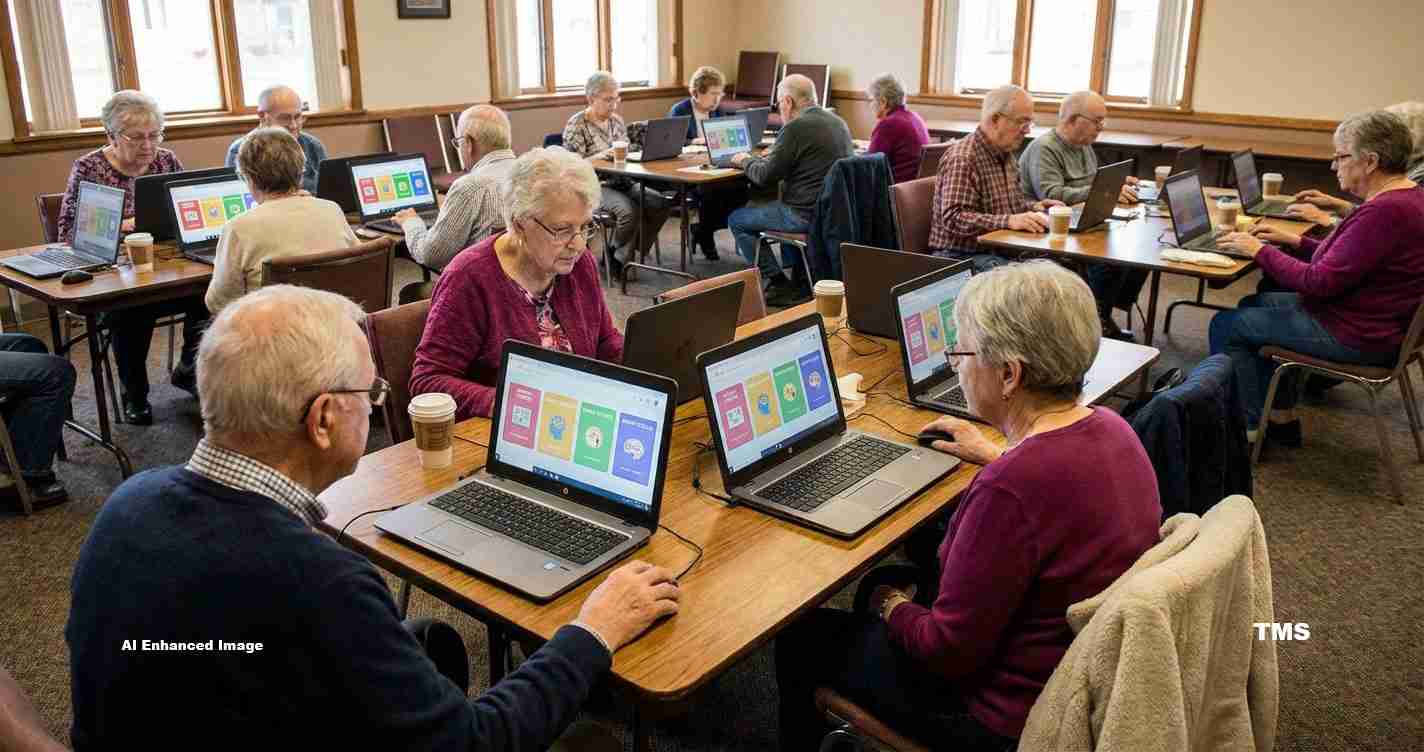
- Speed of processing: Computer-based visual tasks that adapt to performance to train processing speed and divided attention.
How the follow-up was done
Researchers tracked dementia diagnoses across two decades using medical records and Medicare claims, reducing certain biases common to observational studies. The randomized design and lengthy follow-up increase confidence in the observed effect for speed training with boosters.
Full methods and adjusted risk estimates are detailed in the Alzheimer’s & Dementia report and summarized in the ScienceDaily summary.
Why speed training may work
Speed-of-processing exercises were adaptive: tasks became harder as participants improved, forcing faster information processing and handling of multiple stimuli. Investigators suggest this may strengthen attention and rapid-decision networks, potentially delaying clinical manifestations of dementia.
Voices from the research team and experts
“The durability of the effect is surprising,” said Michael Marsiske, PhD, interim co-chair at the University of Florida Department of Clinical and Health Psychology, noting no signs of harm and the largest benefit among those completing 18 sessions over three years.
Outside experts urged cautious optimism and recommended combining cognitive training with other prevention strategies. For commentary on brain plasticity as a plausible mechanism, see the BrainHQ perspective.
What earlier ACTIVE reports found
At five years, all training groups showed improved ability in everyday tasks (managing money, cooking, medication). At 10 years, reasoning and speed groups still showed cognitive gains; earlier reports suggested ~29% dementia risk reduction for speed training at that mark. The 20-year analysis isolates the speed+boosters group as the only arm with a statistically significant reduction across the full period.
Limitations and remaining questions
Although randomized, the study used medical records and claims data to identify dementia, which can miss subtler clinical details. The biological mechanism linking training to delayed dementia remains not fully understood. Replication, attention to equitable access, and integration with other risk-reduction measures are needed before broad rollout.
Policy and public health implications
These results support the idea that non-drug interventions can contribute to dementia prevention. The NIH highlighted the finding and suggested combining targeted cognitive training with lifestyle and vascular risk control in future trials.
Implications for California
Economic impact: California’s large older-adult population and Medicare enrollee base mean delaying dementia onset even modestly could reduce long-term care costs and caregiver burden. Community-based deployment through senior centers, libraries, or telehealth could be cost-effective if rigorously evaluated.
Political consequences: For a moderate conservative audience, the results support prevention-oriented, cost-saving approaches delivered through public–private partnerships rather than expanded entitlement programs. Any public funding should include rigorous evaluation and focus on targeting high-risk groups.
Social and cultural relevance: Slower cognitive decline preserves independence. Californians who value active aging may favor short, structured programs available via community centers or health plans. Providers should ensure accessibility on tablets/computers and pair training with exercise, healthy diet, and blood pressure control.
Next steps for California providers and families
Health systems, primary care, and aging services can review the ACTIVE protocol and partner with researchers to pilot local programs. Insurers and employers with retiree benefits might consider covering brief, evidence-based speed training. Families should ask clinicians about cognitive training options and combine them with exercise, sleep hygiene, and vascular risk management.